Why patients choose a clinic before they ever call
The direct answer
Patients choose a clinic long before they can evaluate its medicine. Unable to judge clinical skill directly, they judge proxies: the reviews, the name, the premises, and what a search shows after a friend's recommendation. A practice with hundreds of grateful patients and no online record loses exactly the bookings its reputation already earned, because the verification step finds silence. Clinic branding is the deliberate construction of those trust proxies: one clear identity, a credible online record that matches the waiting room, and the consistency that lets a recommendation survive a Google search.
Five conclusions
The argument, compressed.
- Patients judge what they can see because they lack the tools to judge what matters. The proxies are the product until the treatment begins.
- Every recommendation triggers a verification search. A practice invisible at that step leaks the referrals its own patients generate.
- Reviews are a clinic's most undervalued distinctive asset: hundreds of grateful voices, usually left unread on a listing nobody manages.
- Elective and private treatments are chosen like consumer purchases, which makes them brand decisions in a way prescribed care never is.
- A practice named after one doctor carries a succession problem; a practice brand outlives the founder and sells with the building.
Working framework · 5 decisions
The referral chain audit
Every new patient travels the same five links. Walk your own practice through them and the weak link usually announces itself.
Decision 01 / 05
Recommendation
A patient describes you to a friend. Which words do they use? A practice that never decided its own sentence gets described five different ways.
The judgement patients can actually make
A patient choosing a clinic faces a strange problem: the thing that matters most, clinical quality, is the thing they are least equipped to evaluate. Degrees look alike. Procedures are invisible. Outcomes reveal themselves months later. So patients do what every buyer does under uncertainty: they judge the observable and treat it as evidence of the unobservable.
The observable is everything a practice tends to dismiss as cosmetic. The state of the signage. Whether the receptionist's answers match the doctor's. What a Google search returns. How three hundred past patients describe the experience. These proxies carry the decision because nothing else is available to carry it.
This is the quiet argument for clinic branding, and it has nothing to do with logos. Brand work for a practice is the deliberate construction of trustworthy proxies, so the judgement patients can make points toward the quality they will eventually receive.
The asymmetry
Clinical skill is invisible at the moment of choice. The proxies are visible. Patients decide on what they can see.
The referral leak every strong practice has
Good practices grow on recommendations, which creates a comfortable illusion: the work markets itself. But recommendations changed shape. A friend's endorsement now triggers a search, and the search is where the referral either completes or dies. The friend supplies the intent; the screen supplies the verification.
A practice with a full waiting room and an empty online record leaks at exactly this step. The recommended patient finds an unclaimed listing, a competitor advertising above the practice name, or simply nothing, and the warm intent cools into choosing whoever looked credible instead. The painful part: the practice never sees these losses, because the patient never arrives to be counted.
The fix costs less than the leak. A claimed and managed listing, a page that confirms what the friend promised, photographs of real premises and real people, and the same practice description everywhere. Verification succeeds when the screen agrees with the recommendation.
Reviews are the distinctive asset nobody manages
Many clinics sit on hundreds of reviews accumulated over years, an archive of grateful voices no competitor can copy, and treat it as background noise. Read as a strategist reads it, that archive is the practice's strongest distinctive asset: proof, in patients' own words, of the exact reassurances a new patient is searching for.
Managed deliberately, reviews work three jobs. They carry verification, because volume and recency read as safety. They supply language, because how patients describe you is the raw material of positioning that sounds human instead of medical. And they feed every other surface: the phrases patients repeat belong on the website, in the waiting room, and in how the receptionist answers the phone.
The management itself is unglamorous: reply to reviews as the doctor, invite them at the moment of genuine gratitude, and surface the best of them where deciding patients will look. A practice that does only this outperforms most healthcare marketing spend.
- Reply to every review in the practice's voice, including the difficult ones.
- Invite reviews at discharge or follow up, when gratitude is real and specific.
- Quote patient language, with permission, on the pages new patients verify.
- Watch the phrases patients repeat: they are telling you your position.
Elective care is chosen, and chosen care is branded
Prescribed care follows referral pathways and urgency; the patient largely goes where they are sent. Elective care behaves differently. Implants, aligners, skin treatments, physiotherapy programmes, health checks: these are considered purchases, researched and compared like any consumer decision, usually at consumer prices.
This split explains why two practices with equal skill earn unequal revenue. The elective patient compares practices the way buyers compare anything: on clarity, on confidence, on how the options are explained, on whether prices and processes feel honest. The practice that presents its elective work as a clear, named, explained offer wins the comparison against the practice that lists procedures in clinical vocabulary.
For most clinics the elective line is also the margin line, which makes this the commercial heart of practice branding: package the chosen care like it wants to be chosen, and let the prescribed care continue arriving through pathways.
The revenue split
Prescribed care arrives through pathways. Elective care is shopped for. Only one of them rewards brand work, and it is the profitable one.
The doctor's name problem
Most small practices are named after their founder, which works until it constrains. A personal name concentrates trust in one human: it resists delegation, because patients booked the name; it complicates growth, because a second clinician always feels second; and it makes the practice unsellable, because the asset retires with the person.
The alternative carries its own cost. A practice brand takes years to earn the warmth a doctor's reputation already holds, and a rushed rename can spend decades of recognition in a weekend. The honest answer for most clinics is architecture rather than replacement: a practice brand that carries the institution, with the founder's name held inside it as the credibility it is.
When to decide is clearer than what to decide: before hiring the second clinician, before opening the second location, and long before any thought of selling. Architecture chosen under deadline pressure is where practices lose recognition they never recover.
What a credible practice record includes
The record a deciding patient needs is short, and almost none of it is promotional. Who the clinicians are, with faces and credentials stated plainly. What the practice treats, in the patient's vocabulary rather than the profession's. Where it is, when it opens, what happens on a first visit, and what things cost or how pricing is decided. Real photographs, because stock imagery reads as concealment in a category built on trust.
Then the same description everywhere: listing, website, directories, social profiles if any. Health decisions make people sensitive to inconsistency, and a practice described three different ways triggers the exact doubt the record exists to settle.
One boundary matters more in healthcare than anywhere else: credibility work stays inside professional advertising rules, which differ by country and council. The safe ground is the same as the honest ground, and it is wide enough. Clarity about who you are, proof from real patients, and answers to real questions build more trust than any claim a regulator would question.
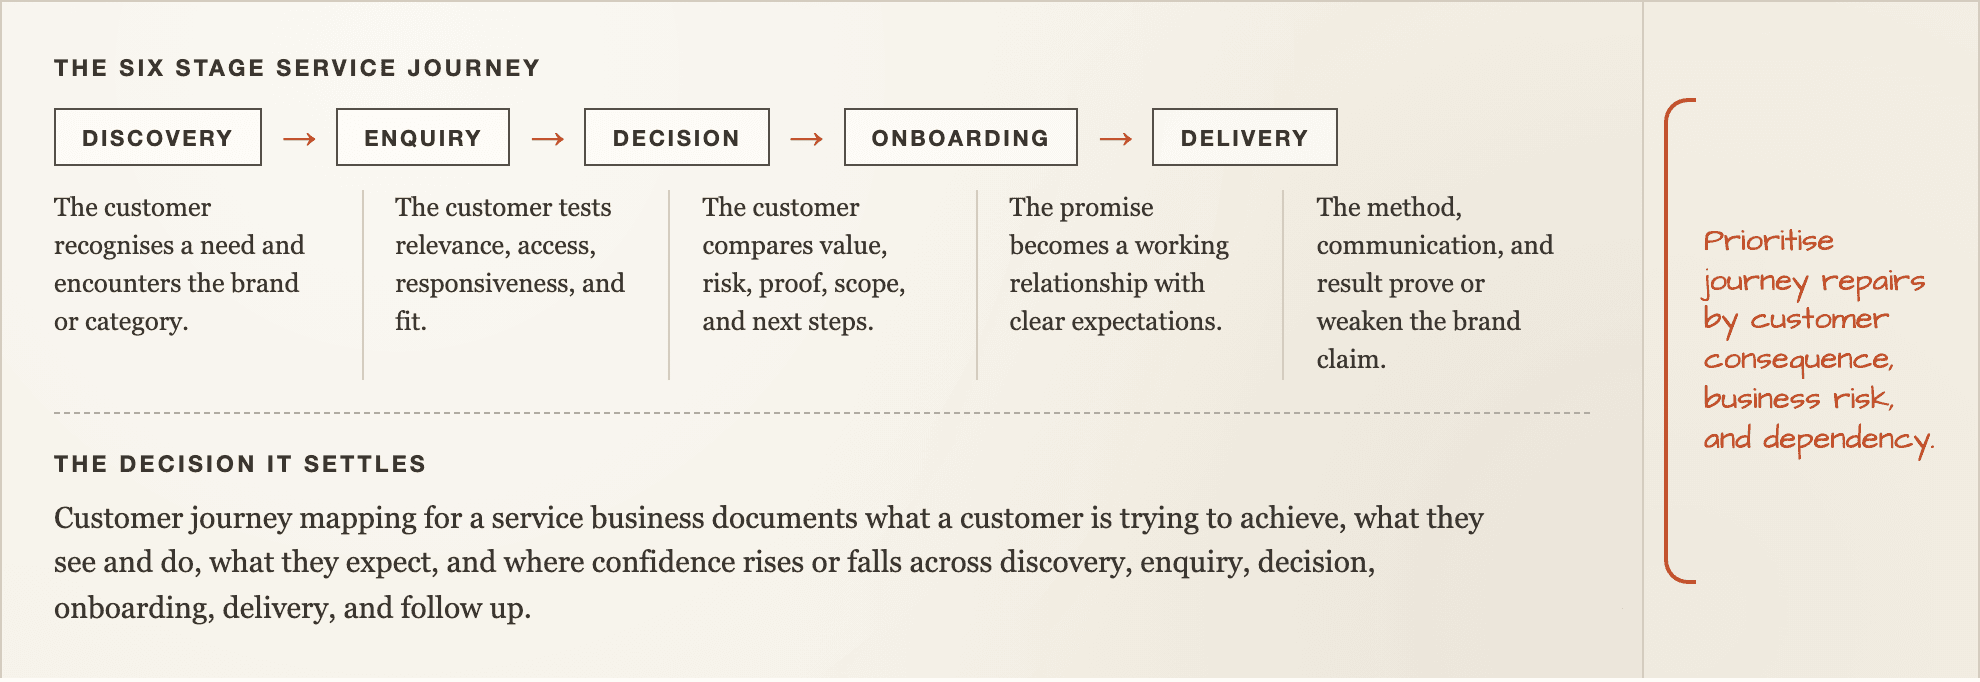
Where a practice begins
Run the referral chain audit from the framework above on your own practice, as a stranger: have a friend search you, read what they find, try to book. The weak link is usually obvious within ten minutes, and it is usually the search or verification step.
Then sequence the work by leverage. Claim and complete the listing first, because it is where every recommendation gets verified. Decide the one sentence that describes the practice and install it everywhere. Put the review archive to work. Package the elective offers in patient language. Settle the naming architecture before growth forces it.
None of this requires a large budget; it requires the same deliberateness the clinical side already runs on. A practice that diagnoses before treating understands this order of work better than most businesses ever will.
Before you use it
Questions that can change the recommendation.
Is branding appropriate for a medical or dental practice?
Understood correctly, yes, and most professional codes point the same way. Branding for a practice means clarity, consistency, and verifiable proof: who the clinicians are, what the practice treats, and what real patients report. Advertising rules differ by country and council, so specific claims always deserve a check against the local code, but honesty about identity sits comfortably inside every one of them.
Does a small clinic with full appointment books need this?
A full book today is the strongest position from which to do the work, and the weakest excuse to skip it. Full books hide the referral leak, cap elective revenue at whatever walks in, and leave the practice exposed the day a well presented competitor opens nearby. Practices that build the record while busy choose their growth; practices that wait respond to someone else's.
What does brand work for a clinic cost?
Published starting figures for this practice sit on the pricing guide: a defined starting engagement from £1,950 in the United Kingdom, $2,800 in the United States, CA$3,200 in Canada, with Indian pricing shown on the services page. For most clinics the defined engagement covers the decisions that matter first: the practice sentence, the record, the review system, and the elective packaging.
Should the practice carry the doctor's name or its own?
Depends on the ten year intention. A practice that will always be one clinician can happily carry the name that built it. A practice that plans associates, locations, or an eventual sale needs an institutional brand, ideally decided early, with the founder's name kept inside it as credibility. The expensive path is deciding under pressure after growth has already arrived.
How is this different from healthcare marketing?
Marketing buys attention; the brand decides what attention finds. A clinic that advertises before fixing its record pays to send sceptical patients toward an unverifiable practice. The order that works runs the other way: decide the identity, build the proof, then let recommendations, search, and any paid activity all land on a record that converts them.